Tattoo Safety: The Hidden Risks of Ink and Health
By Darren Smith, Arts Reporter
September 12, 2026
A long-running assumption in clinic rooms is that once a tattoo heals, the ink simply sits in the dermis like a sealed photograph. That view is being rewritten. Dermatology Times today resurfaced “Under the Needle—Reevaluating Tattoo Safety in the Modern Era,” an essay by Yale dermatologist Christopher G. Bunick, MD, PhD, that gathers newer epidemiology, pigment chemistry, and exam-room practice into one argument: tattoo pigment is not inert. It travels. It lodges in lymph nodes. It can confuse cancer workups. And in some large studies, it tracks with higher rates of lymphoma.
Bunick’s piece is not a panic bulletin. He opens by celebrating the art itself—Hogwarts castles, film portraits, cartoon characters—the visual inventory that makes full-body skin exams one of the more human parts of dermatology. For years the specialty’s tattoo conversation stayed local: regret, allergic reactions, the odd Staphylococcus infection. Prevalence has outrun that frame. So has the research.
The Swedish work that still anchors the debate was published in eClinicalMedicine in 2024. Christel Nielsen and colleagues at Lund University used the national cancer register to identify incident malignant lymphomas diagnosed in people aged 20 to 60 between 2007 and 2017, then matched them to controls and asked about tattoos. After adjustment for education, income, age, and smoking, tattooed people had a 21 percent higher risk of overall lymphoma (incidence rate ratio 1.21; 95 percent CI 0.99–1.48). The signal was strongest for diffuse large B-cell lymphoma and follicular lymphoma. Timing mattered in a distinctive way. Risk peaked in the first two years after a first tattoo (IRR 1.81), eased across years three to ten, then rose again after eleven or more years—a U-shaped curve that looks less like a one-time chemical splash and more like an acute insult followed by long, low-grade immune work. The paper is available in full at PMC. Importantly, the Swedish team did not find a clean dose-response by tattooed surface area, a result Nielsen has said surprised the group.
Denmark added a different design. In a 2025 BMC Public Health analysis of the Danish Twin Tattoo Cohort, Signe Bedsted Clemmensen and colleagues used both a cohort of 2,367 twins and a case–cotwin comparison to tighten control for shared genes and childhood environment. Tattoo ink exposure associated with lymphoma and skin cancers. For tattoos larger than a palm, hazard ratios reached 2.73 for lymphoma and 2.37 for skin cancer. Individual-level cohort estimates were higher still for skin cancer and basal cell carcinoma, though absolute numbers of events were small and confidence intervals wide. That study is open at PMC. Twin methods reduce some confounding; they do not prove causation. Lymphoma remains uncommon. A relative bump from a low baseline is not the same as a common outcome.
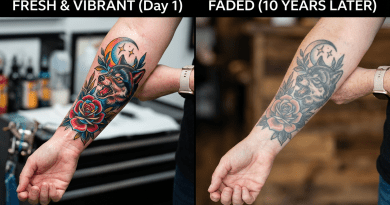
Bunick places those numbers next to what is already known about where ink goes. Macrophages ferry pigment from skin to draining nodes. Porcine work has shown elements reaching nodes quickly and approaching steady state within days. Inks can carry heavy metals, polycyclic aromatic hydrocarbons, and primary aromatic amines. Black inks often rely on carbon black that can contain benzo(a)pyrene. Red azo dyes can cleave into aromatic amines. Ultraviolet light can photodecompose pigments into more reactive fragments. Laser removal shatters particles and may accelerate their trip to nodes—one reason Swedish investigators flagged higher lymphoma rates among people who had lasers used on their tattoos, a finding they treated as a lead for more study, not a verdict.
For dermatologists the practical problem is as immediate as the statistical one. Dense ink hides the ABCDE cues used to catch melanoma. Classic dermoscopic structures of basal cell carcinoma can vanish under exogenous pigment. Bunick’s recommended shift is toward vascular morphology and shiny white structures that still read through ink; toward palpation of blackout fields for induration the eye cannot see; toward earlier confocal microscopy or optical coherence tomography when visual access is poor. Migrated pigment can also mimic metastatic disease on imaging and complicate sentinel-node interpretation, which is why oncology teams already treat tattooed nodes as a staging trap.
None of this requires a ban on body art. It does require honest counseling. Bunick’s list is modest and specific: a baseline full-body exam before new work; a request that artists not tattoo over existing moles or scars; sun protection framed as ink protection, because ultraviolet light is both a DNA hazard and a chemical catalyst; and caution that removal is not a simple undo. National Geographic covered the same scientific turn earlier this year, which is how Bunick’s clinic-floor concerns reached a general audience before Dermatology Times put the specialty synthesis back in circulation today.
The literature is not unanimous on skin cancer. French and Utah case-control papers and a Dutch registry analysis have produced mixed melanoma results, some even hinting that people who sit for many sessions might show different patterns—possibly selection, surveillance, or chance. That inconsistency is why responsible writing refuses a single headline. What is consistent is mechanics: pigment leaves the skin, lymph nodes collect it, some ink constituents are biologically active, and two Northern European studies found lymphoma associations that survive basic confounder adjustment.
Regulation still lags the science. Ingredient lists vary by country and by bottle. “Professional” does not automatically mean toxicologically mapped. Artists already live inside hygiene rules; they are not the target of this literature. The target is a gap between a booming cultural practice and a slower medical update cycle.
Patients who already have tattoos should not read this as a demand to panic or to strip ink off in a rush. They should read it as a reason to keep skin checks, mention tattoo history at oncology visits, protect pigmented skin from ultraviolet breakdown, and treat new work as a medical-adjacent decision rather than only an aesthetic one. Clinicians should read it as a reason to put lymph-node palpation back into the exam of heavily tattooed patients and to stop treating ink as a purely cutaneous footnote.
The art is still art. The pigment is also chemistry in motion. Dermatology Times putting Bunick’s synthesis in front of readers again today is a reminder that the two facts now belong in the same sentence.
If you have tattoos or are planning one, book a full-body skin exam, ask your artist not to work over moles, and talk with a dermatologist about photoprotection and node checks before you add more ink.
Cover image is AI-generated and used for illustration only.